Colorectal Cancer Screening and Management (CRCSM) Clinical Decision Support (CDS) Implementation Guide - Local Development build (v0.1.0) built by the FHIR (HL7® FHIR® Standard) Build Tools. See the Directory of published versions
Background
Background
Primary care providers typically are responsible for scheduling screening tests. Both breast and colorectal cancer screening potentially could be improved by computerized electronic health record (EHR) prompts for patients and providers when screening tests need to be scheduled. In addition, depending on the test and finding, a patient and their care team may need to track when follow-up testing is needed, from several months to many years.1 Successful screening for breast and colorectal cancer relies on timely follow-up after an abnormal test result.2 3
To encourage adoption of cancer screening guidance and rapid dissemination of updated practices based on the latest guidance, CDC's Division of Cancer Prevention and Control (DCPC) supports the development and implementation of vendor-neutral clinical decision support (CDS) tools for integration into health information technology (IT) systems such as EHRs. These CDS tools can take shape in a variety of forms (e.g., reminders, visual displays, order set recommendations, complex risk calculations) in clinician EHRs or patient portals to inform the appropriate care recommendations that lead to improved screening outcomes and management of abnormal test results.
CDC in partnership with the Health FFRDC will develop, implement, and disseminate computable guidelines for breast and colorectal cancer screening and management. The project is focused on the development of CDS tools to support clinician adherence to advances in breast and colorectal cancer screening and management guidelines.
Project Overview
The Health FFRDC is developing interoperable CDS tools to increase awareness and adoption of colorectal cancer screening and management (CRCSM) guidelines. The tools will assist clinicians with identifying individuals due for screening and manage care concordant with clinical practice guidelines. The CDS tools are being developed using international health IT standards to support interoperability and a modular approach to facilitate adaptation, configurability, and future updates. The project includes the following activities:
-
Environmental Scan for Breast and Colorectal Cancer Guidelines: Conduct an environmental scan to determine the full scope and application of screening and management clinical practice guidelines for both breast and colorectal cancer. The scans for these two cancers will be conducted independently so that both cancers are fully understood. Look broadly across the guideline organizations and the latest evidence-based clinical guidelines to determine an appropriate set to translate into computable form. Identify existing efforts and best practices for translating those guidelines into clinical practice. Elicit input from subject matter experts and relevant stakeholders where appropriate.
-
Logical Representation of Practice Guidelines: Translate the narrative form of the screening and management clinical guidelines into semi-structured form that accurately captures the data elements and logical pathways described in the unstructured documents. Complete the first stage of the knowledge translation process to CDS Level 2 representation which is a human readable semi-structured expression of the breast and colorectal screening guidelines. The desired and appropriate set of practice guidelines designated for translation is determined in Task 1.
-
CDS Tools for Breast and Colorectal Cancer: Determine the design, features, and desired utility of the CDS tools for the two cancers. For example, the CDS can provide cognitive support to clinicians, promote clinician/patient engagement, and support patient-facing features. Apply CDS modular framework, developed for prior CDC funded effort for cervical cancer, to create executable CDS tools to support screening and management of breast and colorectal cancer.
Overview of Clinical Decision Support
The primary goal of this project is to develop CDS tools that provide clinicians and patients with the best evidence-based clinical guidance to inform their care decisions for cancer screening and any necessary follow-up care. Clinical guidelines are published by professional guideline organizations as a journal article in narrative form. Clinical guidelines for cancer screening and management are increasingly complex and require a baseline patient risk assessment to determine the appropriate screening age, modality, and frequency. CDS tools and interventions that are derived from a computable representation of the narrative guidelines enable a digital lifecycle to get the most recent evidence into practice faster, which will ultimately improve health outcomes.
What Is Clinical Decision Support?
CDS is a critical tool in healthcare that aids clinicians, staff, patients, and other individuals by providing person-specific information, intelligently filtered or presented at appropriate times, to enhance health and healthcare. CDS tools enhance decision making in the clinical workflow and can manifest in a variety of forms:
-
Computerized alerts and reminders
-
Clinical guidelines
-
Condition-specific order sets
-
Focused patient data reports and summaries
-
Documentation templates
-
Diagnostic support
-
Contextually relevant information
CDS tools typically operate as a collection of interoperable system components, usually within an EHR. These components are represented in computable formats designed to support the clinical workflow. CDS components often include triggers, knowledge collection, and actions.
CDS triggers are the events that "trigger" a decision support rule to be invoked. Such events might include the ordering of a cancer screening or the prescription of a drug. Once a trigger has been invoked, knowledge collection of data elements for the patient may occur. In the context of breast or colorectal cancer, relevant data elements to be collected may include patient demographic data, patient and family health histories, prior screening data, and laboratory results. Actions, or interventions, are the result of a CDS trigger. Examples of actions include presenting a guideline to the primary care physician (PCP), making a recommendation based on a calculation from knowledge collection, or presenting an alert to the PCP such as a missed patient cancer screening.
When discussing CDS components, particularly in detail, clinical concepts are usually expressed with standard terminologies (SNOMED, LOINC, ICD10, etc.). The executable logic used by CDS to execute an action is often represented by the Clinical Quality Language (CQL), a Health Level 7 (HL7) standard for querying against clinical data gathered during knowledge collection.
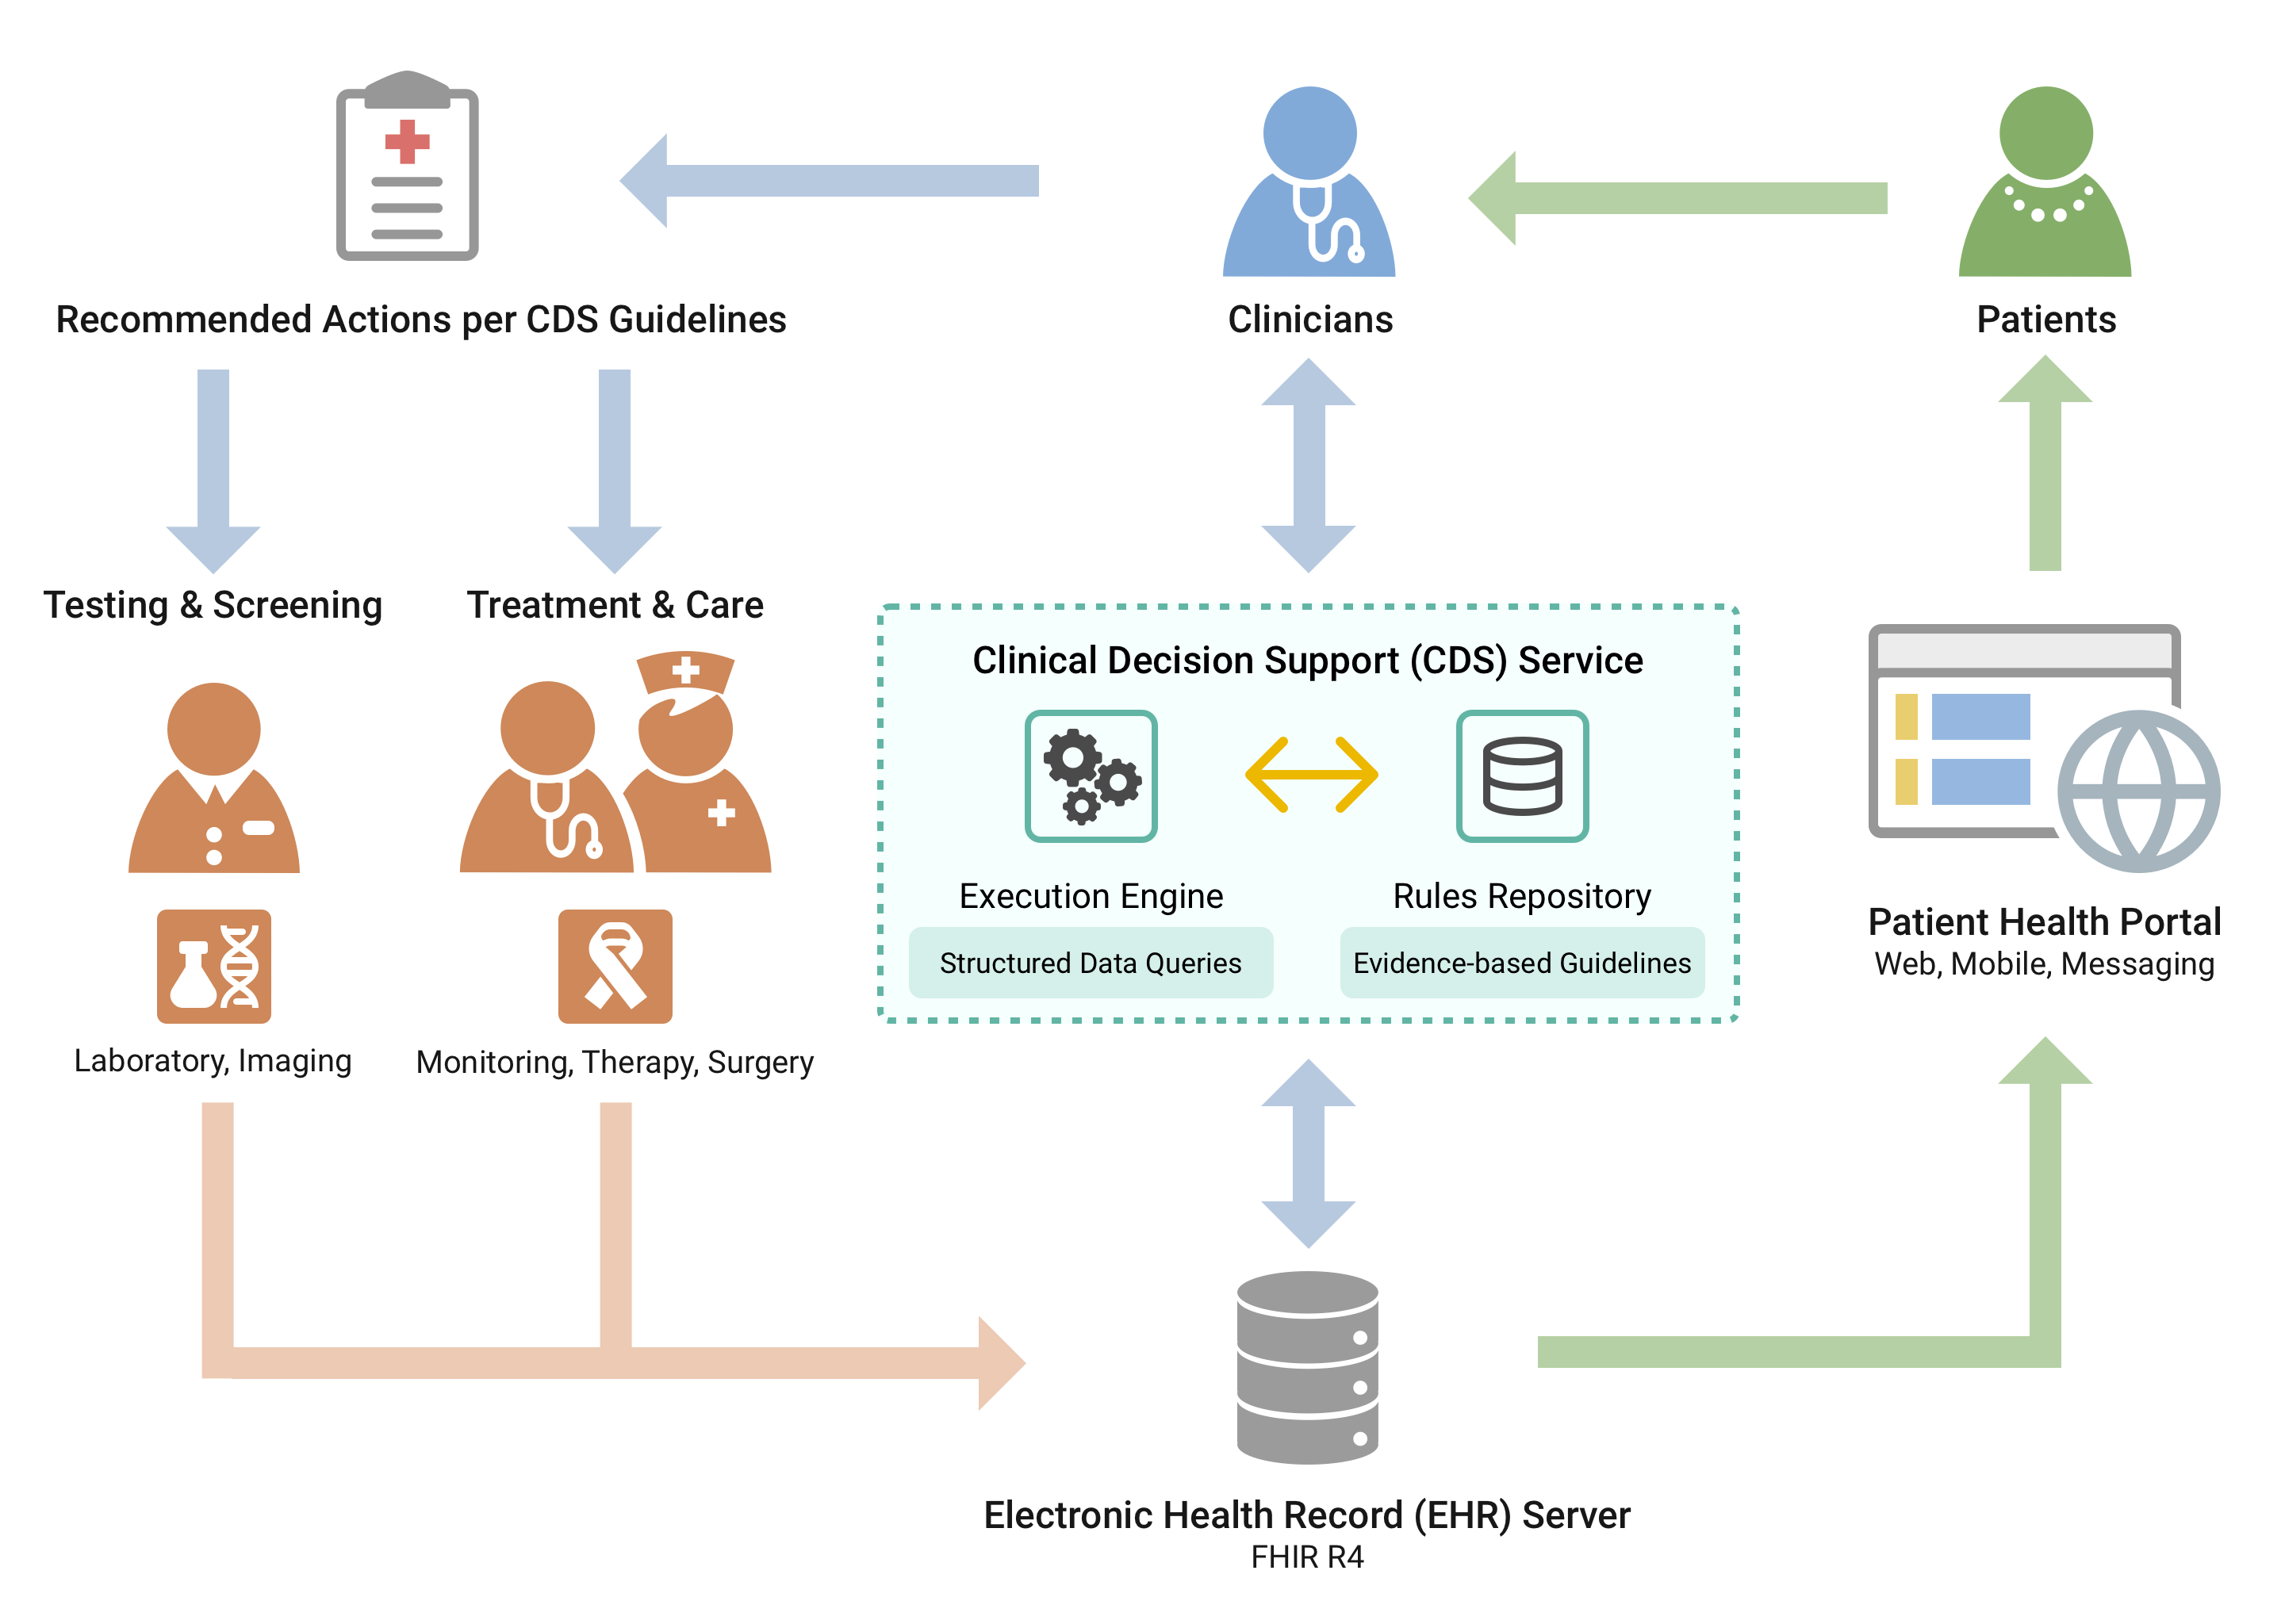
Figure 1: Clinical Decision Support Conceptual Workflow
Figure 1 above illustrates the workflow and interaction with the CDS in a clinical setting:
-
Patient information flow is shown in green. The patient health portal represents patient-facing interactions with their health data, and could utilize web access, a mobile app, or messaging services.
-
Clinician information flow is shown in blue. The clinician interacts with the CDS service, which queries the EHR server for patient data.
-
Screening and treatment providers are shown in brown. These represent laboratory services, cancer specialists, surgeons, or other specialized care providers.
-
The results of all health actions are recorded in the EHR server. These results can further inform the CDS service, other clinicians, and the patient health portal.
CDS Interaction: How CDS Is Used
The CDS tool itself is just a service. It needs an interface to communicate with the clinician, patient, or others who interact with the CDS. The CDS is designed using a modular component approach to improve interoperability, maintainability, and reusability. CDS components can be created once, reused in multiple EHRs, or adapted for stand-alone applications with less redundancy and more consistency. Some level of configuration is always required to adapt to specific clinical workflows, vendor-specific requirements, or constraints of the implementation.
CDS Integration: How EHR Invokes CDS
The use of Fast Healthcare Interoperability Resources (FHIR) standards for the CDS service allows it to be integrated into existing tools, such as EHR systems using the CDS Hooks™ standard, or to be built into custom applications that communicate with other health IT applications and services using the SMART-on-FHIR® API (application programming interface). By using these two standard approaches, the CDS can be implemented as an interoperable service for use with certified EHRs that require support for FHIR-based CDS integration.
CDS Modular Design
A modular approach is central to the design and implementation of this CDS to support the clinical needs mentioned above. A modular approach offers several benefits in terms of interoperability, adaptability, and reusability. Building individual components as part of this project allows for the components to be assembled in multiple ways to address different use cases (e.g., clinical and quality improvement needs). Each use case will have its own specific requirements related to the system or workflow it is intended to work with. As with any interoperable approach, these modular components will be assembled into an operational CDS application and configured (with additional integration code) to work with or within a health IT system.
Taking this type of modular approach is not new, and it is not novel to the Health FFRDC. There are many organizations that build CDS systems this way and many examples of these modular approaches. For more on this modular approach to CDS, see the FHIR Clinical Guidelines IG.
CDS Integration in EHR
Integration refers to the process of incorporating a CDS for use within a health IT system; it can occur any time after initial CDS testing has concluded. This section outlines a process for integrating the CRCSM CDS. It starts with a description of the health IT interoperability standards needed for integration. These standards provide multiple options for how the CRCSM CDS can be integrated into a health IT system. Those options are discussed as are the high-level requirements for what a health IT system needs to provide in order to support integration. A necessary CDS integration activity called "data mapping" is described next. This CDS Integration concludes with a listing of strategies for handling unstructured data which the CRCSM CDS may need to have access to.
Interoperability Standards for CDS Integration
The interoperability standards described in Section 3.3.1 have been used to define the CRCSM CDS in an open and shareable format. This section describes additional standards which aim to help support CDS integration into a health IT system.
Sustainable Medical Applications, Reusable Technologies (SMART®)
The Sustainable Medical Applications, Reusable Technologies (SMART®) standard facilitates the integration of software applications, or "apps," with health IT systems. "SMART on FHIR apps," or sometimes simply "SMART apps," are software applications that securely interact with patient EHRs and other healthcare-related data via a FHIR API. SMART apps are interoperable in the sense that they can interface with any health IT system that supports the SMART standard and the data requirements of the app. Instead of writing a separate software application to provide the same capability for each different health IT system, a single application can be written that works with many different health IT systems.
A key component of SMART has been documented in the SMART App Launch IG. It is the sequence of steps taken so that an app can be authenticated and authorized by a health IT system before any FHIR resources are accessed. This SMART App Launch Framework helps to ensure that a particular SMART app is granted access to only the EHR data that it needs and that its user is authorized to access. Some of the CRCSM CDS integration options presuppose that SMART will be available in the system to which it is to be integrated. Without SMART, a custom interface would have to be designed for each health IT system, which defeats the intent and benefit of interoperable CDS. Fortunately, SMART has been specifically called out as a requirement for certified EHRs in the ONC 21st Century Cures Act Final Rule. Many EHR vendors already support SMART.
CDS Hooks
The CDS Hooks standard describes how CDS services, which are simply software that provide CDS, can be integrated with health IT systems. While SMART is more general in nature, CDS Hooks focuses on integrating CDS into the clinician workflow. This is accomplished through the use of a number of so-called "hooks," which is a software term for a technique for altering the behavior of a software program. CDS Hooks focuses on how CDS recommendations can be sent to a health IT system via informational "cards." In contrast with SMART, a CDS Hooks integration would typically assume that some other system (e.g., the health IT system) would be responsible for displaying the information in these cards to the clinician. This distinction is discussed further in the next section.
Integration Options
This section describes three integration options for the CRCSM CDS using SMART and/or CDS Hooks. These options are based upon the different approaches taken by SMART and CDS Hooks, as depicted below in Figure 2, for integrating CDS into a health IT system. With the SMART on FHIR approach, the CDS application is typically responsible for displaying any content and recommendations to the user. With CDS Hooks, that content and recommendations are typically sent back to the health IT system, which is then responsible for displaying it.
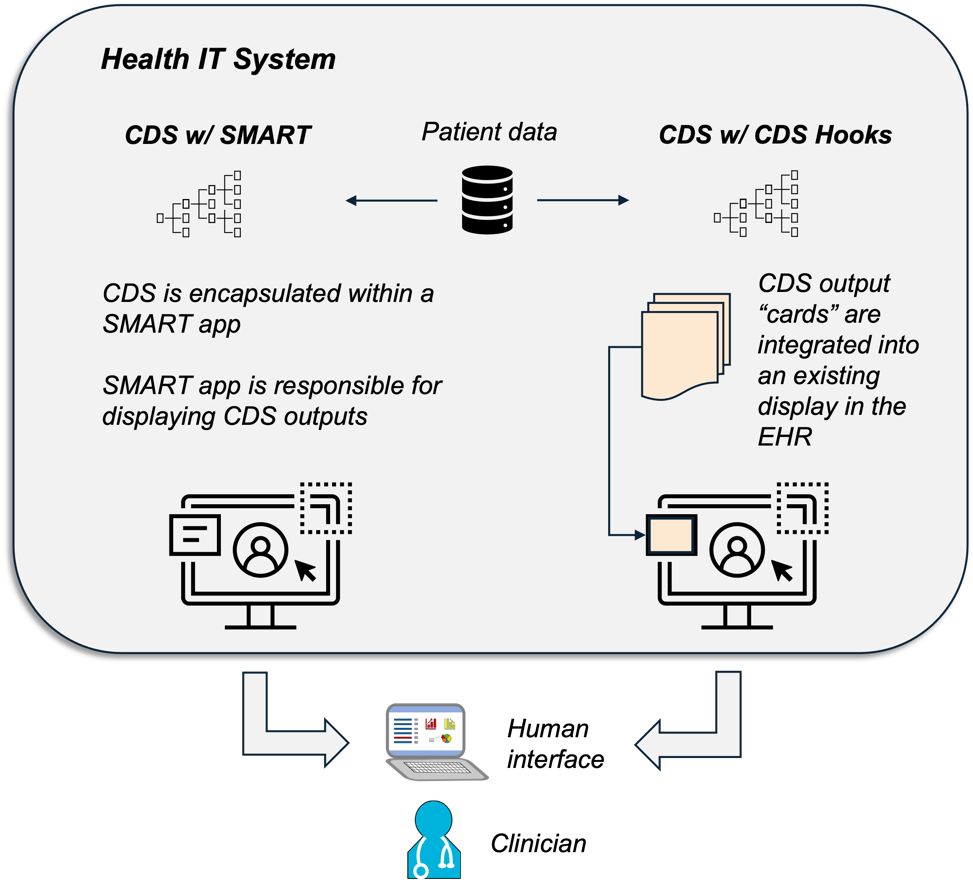
Figure 2: Diagram showing integration approaches taken by SMART and CDS Hooks.
Option 1: SMART
The first integration option entails embedding the CRCSM CDS into a standalone SMART on FHIR application. The SMART application can be launched from the health IT system but must then query the EHR for the patient data required by the CDS. Once the required data has been pulled from the EHR, it is used along with the CDS definition as part of the FHIR $apply operation. The outputs from the FHIR $apply operation are then used to populate the CRCSM dashboard and present the clinician with recommendations. If the clinician chooses to act on the recommendations, the SMART application must transmit the confirmed intervention back to the EHR.
The benefits of this integration option include the fact that the CDS is entirely self-contained and has control over the presentation of the CDS outputs. The drawbacks of this integration option include the fact that the clinician has to "leave" the native health IT system in order to interact with the CDS. Also, all CDS software must be bundled within a single application, which may be computationally inefficient. Finally, if the SMART application containing the CDS is hosted apart from the health IT system, there may be latencies associated with data transfer which may impact the user experience.
Option 2: CDS Hooks
The second integration option involves operating one or more CDS Hooks services which implement the CRCSM CDS. As with the first integration option, patient data is accessed via a FHIR API. However, the results from evaluating the FHIR $apply operation are returned back to the health IT system which triggered the CDS. These CDS outputs are returned in the form of one or more cards, which are just a standardized format defined by CDS Hooks. The health IT system is responsible for presenting the output cards to the user.
One advantage of a purely CDS Hooks approach is that the CDS outputs can be integrated more naturally into the health IT system display. This may help users become more comfortable with using the CDS. Additionally, the user does not have to "leave" the health IT system to use the CDS, which has both user experience as well as latency benefits. Finally, the second integration option provides better flexibility in terms of how the CDS software is structured. The main disadvantage of the second integration option is that there little to no control over how the CDS outputs are displayed to the user. Also, interactive CDS (user provides inputs after the CDS initially triggers) may be harder to implement with a purely CDS Hooks approach.
Option 3: CDS Hooks and SMART
The third integration option involves combining the CDS Hooks and SMART approaches. The initial CDS trigger and inclusion logic is handled via a CDS Hooks service, which returns a card to the health IT system containing a link to a SMART app. This SMART app is responsible for part of the CDS logic as well as displaying the CDS outputs to the user. The third integration option has many of the advantages and disadvantages of the first two options, with the additional disadvantage of being more complex to implement. The third integration option would be appealing to implementors that already have a CDS Hooks capability but want to have more flexibility with how interaction with the user is handled.
Requirements
This section provides some high-level requirements for integration of the CRCSM CDS into a health IT system. Functional requirements are discussed first, followed by data requirements.
Functional Requirements
A health IT system for which the CRCSM CDS application will be integrated must support the following capabilities:
-
Read access of required patient data via FHIR API (see Section 3.4.3.2)
-
Write access via FHIR API (outputs of $apply operation)
-
SMART app launch (if using integration options #1 or #3)
-
CDS Hooks services (if using integration options #2 or #3)
-
FHIR $apply operation
-
CQL execution capabilities
The last two requirements may be fulfilled with the help of the testing software listed in Section 3.4.3. There are other open sources tools which may help address the other requirements.
Data Requirements
The CRCSM CDS must by definition make certain assumptions about what data will be available in the patient EHR. These assumptions are represented by a set of data requirements consisting of the type of data required, how that data will be represented using FHIR, and what clinical informatic code(s) will be used. The data requirements are defined by the FHIR queries performed within the CQL logic of the CRCSM CDS.
Data Mapping
It is expected that most health IT systems will not meet all data requirements discussed in Section 3.4.3.2. Data mapping is the process of transforming some or all of the data in a health IT system such that the data requirements of the CDS are satisfied. Data mapping can be the most time-consuming aspect of CDS integration; it is recommended that both clinical and technical resources be available to support it. Without a proper data mapping, the CDS may fail to locate all the patient data necessary for proper operation.
For health IT systems without a FHIR API, the first step in data mapping would be implementing a FHIR API that is accessible to the CDS. For health IT systems with an existing FHIR API, there may some types of FHIR resources which are needed by the CDS but that are not supported by the API. In this case, the next step would be to add support for the missing FHIR resource types, either by directly augmenting the FHIR API or via an additional "interoperability layer." Finally, the health IT system's FHIR API may support all necessary FHIR resources, but the FHIR resources may not use the same clinical codes employed by the CDS. In this case, the codes used in the health IT system must be converted, or "mapped," to the codes assumed by the CDS.
Handling Unstructured Data
Despite best efforts through data mapping, there may still be information needed by the CRCSM CDS which will not have the required structure as FHIR resources. This section describes approaches for handling so-called unstructured data, which can include information from anatomic pathology laboratory systems.
Allow Clinician Input
A key aspect of the CRCSM CDS is to, when necessary, allow clinicians to provide input to augment the information in the patient EHR. Clinician input is captured using a FHIR Questionnaire resource, which allows a structured set of questions and available responses to be represented in a standard format. The FHIR Questionnaire is being developed in conjunction with the CRCSM CDS. The advantage of this approach is that it allows clinician judgement to be leveraged and incorporated into the CRCSM CDS logic when information in the patient EHR is lacking. The disadvantage of this approach is that it requires additional time and effort from the clinician.
A Natural Language Processing (NLP) Application Programming Interface (API)
Natural Language Processing, or NLP, is a technology that among other things attempts to extract knowledge from unstructured or textual narrative data. NLP has been applied to a number of areas in the healthcare domain, including interpretation of anatomic pathology laboratory reports such as cervical cytology reports. This section describes an approach for allowing information from existing NLP algorithms to be incorporated into the CRCSM CDS.
CDS Hooks provides a mechanism in which outputs from existing NLP algorithms can be leveraged by the CRCSM CDS. A CDS Hooks service can be setup which would trigger when new unstructured data is created in the EHR. The data would be wrapped in a FHIR resource and sent via a CDS Hooks API to the NLP service. The data would be unpacked and processed by the NLP algorithm; CDS Hooks and the FHIR Clinical Reasoning Module provide a process by which the NLP outputs can be ingested back into the EHR as FHIR resources. This can be done in such a way that the CRCSM CDS can accurately leverage the knowledge provided by the NLP algorithm.
-
Atlas SJ, Tosteson ANA, Wright A, et al. A Multilevel Primary Care Intervention to Improve Follow-Up of Overdue Abnormal Cancer Screening Test Results: A Cluster Randomized Clinical Trial. JAMA. 2023 Oct 10;330(14):1348-1358. doi: 10.1001/jama.2023.18755. PMID: 37815566. ↩
-
Reece JC, Neal EFG, Nguyen P, McIntosh JG, Emery JD. Delayed or failure to follow-up abnormal breast cancer screening mammograms in primary care: a systematic review. BMC Cancer. 2021 Apr 7;21(1):373. doi: 10.1186/s12885-021-08100-3. PMID: 33827476; PMCID: PMC8028768. ↩
-
Zorzi M, Battagello J, Selby K, Capodaglio G, Baracco S, Rizzato S, Chinellato E, Guzzinati S, Rugge M. Non-compliance with colonoscopy after a positive faecal immunochemical test doubles the risk of dying from colorectal cancer. Gut. 2022 Mar;71(3):561-567. doi: 10.1136/gutjnl-2020-322192. Epub 2021 Mar 31. PMID: 33789965; PMCID: PMC8862019. ↩